

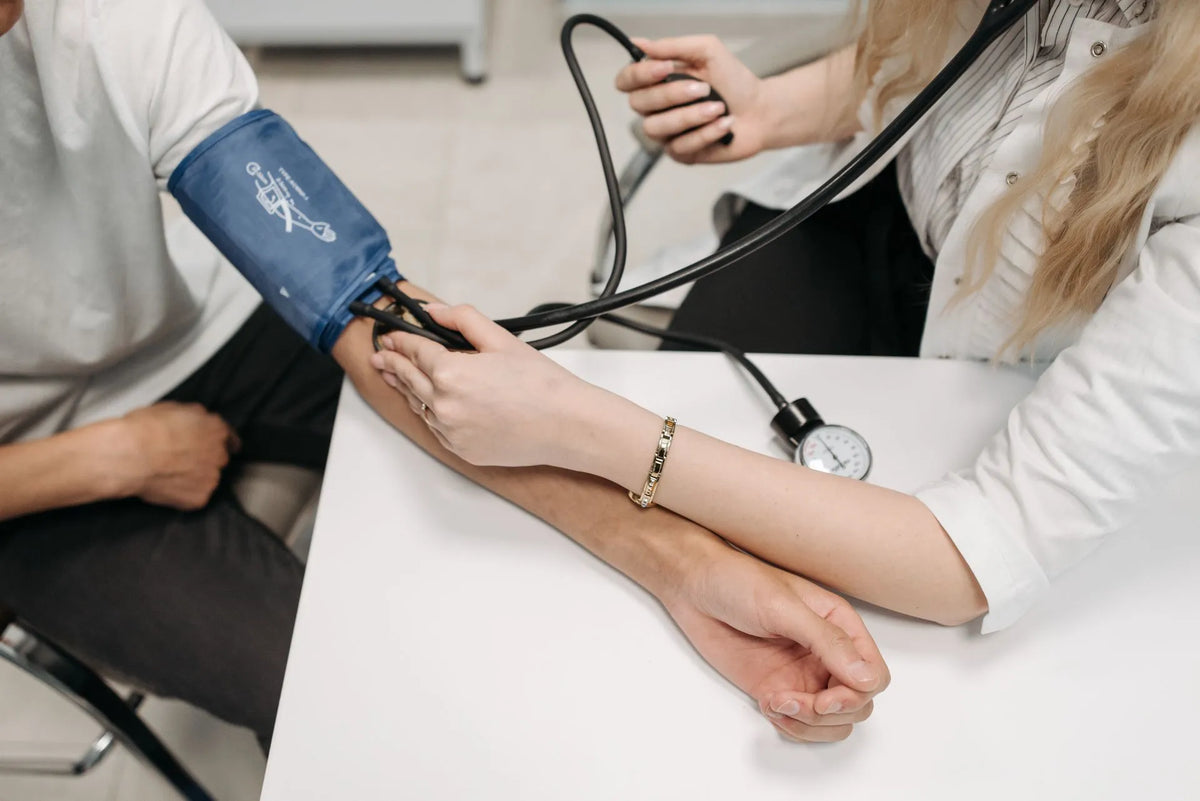
Yes. The FDA confirmed in February 2025 that ambulatory blood pressure monitoring showed a class-wide increase across all testosterone replacement products. The agency added a blood pressure warning to every testosterone label and removed the previous cardiovascular black-box warning following the TRAVERSE trial data (FDA, 2025; Lincoff et al., 2023). The size of the rise depends on the specific product, the client's baseline health, and how closely a provider monitors treatment.
That doesn't mean testosterone replacement therapy (TRT) is unsafe. It means blood pressure monitoring belongs in every TRT protocol, right alongside hematocrit and CBC draws. This article breaks down the product-specific data, explains who carries the most risk, and covers what to track at home and in the lab.

How Much Does TRT Raise Blood Pressure?
The answer varies by formulation. The FDA required ambulatory blood pressure monitoring (ABPM) studies for each testosterone product, and the results ranged from under 2 mm Hg systolic to nearly 5 mm Hg. None of these studies were head-to-head comparisons, so the differences reflect separate trial populations and protocols, not direct superiority of one product over another.
Here are the 24-hour ABPM results from the 2025 prescribing information updates:
|
Product |
Systolic Change (mm Hg) |
Diastolic Change (mm Hg) |
Timeframe |
|
Jatenzo (oral) |
+4.9 |
+2.5 |
4 months |
|
Tlando (oral) |
+4.3 |
not reported separately |
~16 weeks |
|
Xyosted (subcutaneous) |
+3.9 |
+1.5 |
12 weeks |
|
AndroGel 1.62% (transdermal) |
+1.9 |
+1.3 |
16 weeks |
|
Kyzatrex (oral) |
+1.7 |
+0.6 |
4-6 months |
In the Jatenzo study, men already taking blood pressure medication saw a larger increase: +5.4/+3.2 mm Hg. In the Xyosted 1-year trial, 10% of participants either started a new blood pressure medication or changed their existing one (FDA, 2025).
A shift of 2-5 mm Hg may sound small, but population-level data show that even a 2 mm Hg increase in systolic pressure is associated with approximately 10% higher stroke mortality and 7% higher cardiovascular mortality (Lewington et al., 2002). For a man whose baseline blood pressure already sits in the elevated range, a 5-point increase can push readings into stage 1 hypertension territory.
What Does the TRAVERSE Trial Show About TRT and Heart Health?
The TRAVERSE trial is the largest randomized cardiovascular safety trial for testosterone to date. It enrolled 5,246 men aged 45-80 with confirmed testosterone deficiency and preexisting or high cardiovascular risk. They received either AndroGel 1.62% or placebo (Lincoff et al., 2023).
The primary cardiac result was neutral. Major adverse cardiac events (MACE) occurred in 7.0% of the testosterone group versus 7.3% of the placebo group (hazard ratio 0.96, 95% CI 0.78-1.17). That met the noninferiority threshold.
But the trial also found secondary signals that matter:
-
Office systolic blood pressure rose +0.3 mm Hg on testosterone versus a -1.5 mm Hg drop on placebo through 6 months
-
Atrial fibrillation: 3.5% on testosterone versus 2.4% on placebo
-
Pulmonary embolism: 0.9% versus 0.5%
-
Acute kidney injury: 2.3% versus 1.5%
Citing TRAVERSE as a blanket safety endorsement misrepresents the data. The neutral primary endpoint is real, but these secondary findings - atrial fibrillation, pulmonary embolism, kidney injury - require honest disclosure (Lincoff et al., 2023).
Why Does Testosterone Affect Blood Pressure?
3 mechanisms are thought to account for most of the effect.
Red blood cell production. Testosterone stimulates erythropoiesis in the bone marrow. More red blood cells increase hematocrit (the percentage of blood volume occupied by red cells), which raises blood viscosity. Thicker blood requires more force to move through vessels, and blood pressure can rise as a result. The Endocrine Society's 2018 guideline identifies elevated hematocrit as a threshold for clinical intervention, including dose adjustment or therapeutic phlebotomy (Bhasin et al., 2018). A 2025 retrospective study found that 23% of men on TRT developed elevated hematocrit, and 5% reached levels warranting clinical intervention (Neidhart et al., 2025).
Sodium and water retention. Testosterone can shift how the kidneys handle sodium and water. Greater sodium reabsorption can expand blood volume, potentially increasing pressure on vessel walls. This effect can be dose-dependent and tends to be more pronounced in the first weeks to months of treatment.
Vascular tone. Testosterone affects endothelial function and nitric oxide signaling, which govern how much blood vessels dilate or constrict. The net direction of this effect varies by dose, individual genetics, and whether testosterone levels sit in the deficient, physiologic, or supraphysiologic range.
Does Low Testosterone Also Affect Blood Pressure?
Low testosterone is associated with increased cardiovascular risk. Men with clinically low levels have higher rates of central obesity, metabolic syndrome, and type 2 diabetes, all of which are independently associated with elevated blood pressure (Corona et al., 2011). Some observational studies report that men with low testosterone face higher cardiovascular mortality than men with levels in the normal range.
A 2024 observational registry of testosterone undecanoate injections reported office blood pressure reductions, with a median systolic drop of -12.5 mm Hg in men who were not taking antihypertensive medication (World J Mens Health. 2024;42(4):749-761). That registry used office blood pressure measurements, not ambulatory monitoring, and was not randomized. The FDA's class-wide finding, based on ambulatory monitoring from controlled studies, is the labeling evidence.
The takeaway: treating a diagnosed testosterone deficiency may improve metabolic risk factors that contribute to blood pressure. But TRT is associated with a measurable average blood pressure increase that requires monitoring regardless of the underlying benefit.

Who Carries the Most Risk for Blood Pressure Increases on TRT?
Not every man on TRT sees the same degree of change. A 2024 double-blind, randomized, placebo-controlled trial published in the Journal of Hypertension found that the impact of testosterone on daytime ambulatory blood pressure was amplified by baseline BMI and hematocrit levels (Olesen et al., 2024). 2 groups were more likely to experience blood pressure increases while on testosterone:
-
Men with obesity
-
Men with already elevated hematocrit levels at baseline
Other clinical risk factors include:
-
Preexisting hypertension or borderline-elevated blood pressure
-
Sleep apnea (the Endocrine Society's 2018 guideline lists untreated severe obstructive sleep apnea as a contraindication to starting TRT)
-
Kidney disease or reduced kidney function
-
Concurrent use of medications that raise blood pressure (NSAIDs, decongestants, certain antidepressants)
Men with these risk factors may benefit from baseline lab testing before starting testosterone and more frequent monitoring in the initial months of therapy, as determined by their prescribing provider.
How to Monitor Blood Pressure on TRT
Blood pressure monitoring on TRT should happen at home, not just at provider visits. White-coat hypertension (elevated readings in a medical setting that normalize at home) and masked hypertension (normal readings at the provider's office with elevated readings at home) are both common enough to make office-only measurement unreliable.
An upper-arm cuff monitor is more accurate than a wrist device. For consistent readings:
-
Measure at the same time each day, ideally morning and evening
-
Sit upright with feet flat on the floor for 5 minutes before measuring
-
Rest the arm on a flat surface at heart level
-
Take 2 readings 1 minute apart and record both
-
Bring the log to every provider visit
The American Heart Association classifies blood pressure into 4 categories: normal, elevated, stage 1 hypertension, and stage 2 hypertension. A prescribing provider can explain where a given reading falls and what it means in the context of TRT.
A sustained pattern of readings above a client's individualized target warrants a conversation with the prescribing provider. A single high reading doesn't necessarily mean a protocol change, but a pattern over several days does.
Beyond blood pressure, regular blood work that includes hematocrit, a lipid panel, estradiol, and PSA is standard on TRT. The AUA recommends checking hematocrit before starting therapy and at each follow-up visit (Mulhall et al., 2018). If hematocrit rises above guideline-recommended thresholds, a provider may recommend dose adjustment, a change in delivery method, or therapeutic phlebotomy.
What Can Lower Blood Pressure While on TRT?
Lifestyle modifications are commonly recommended for managing blood pressure on testosterone, and providers may recommend addressing modifiable risk factors before starting TRT.
Aerobic exercise. 150 minutes per week of moderate-intensity activity (walking, cycling, swimming) is the standard recommendation. A meta-analysis across 391 randomized trials found that exercise interventions lowered systolic blood pressure by a mean of 5 mm Hg (95% CI: 4-6 mm Hg) compared with control conditions (Naci et al., 2019).
Sodium reduction. The DASH diet (Dietary Approaches to Stop Hypertension) recommends reducing sodium intake, with lower targets for those with elevated blood pressure. The diet emphasizes fruits, vegetables, whole grains, and lean protein while limiting processed foods.
Sleep quality. Consistently sleeping fewer than 7 hours per night is associated with increased blood pressure. Sleep apnea, which the Endocrine Society lists as a contraindication to TRT when severe and untreated, can compound both the blood pressure risk and the hematocrit risk from testosterone.
Hydration. Adequate water intake supports kidney function and helps counteract the blood-thickening effect of elevated hematocrit. There's no single target number, but dehydration can worsen the viscosity increase from erythrocytosis.
Weight management. Excess body fat - visceral fat in the abdomen above all - raises blood pressure through multiple pathways: increased blood volume, higher sympathetic nervous system activity, and impaired kidney sodium handling. Men with obesity were among the higher-risk group for TRT-related blood pressure increases in the 2024 Journal of Hypertension trial data (Olesen et al., 2024).
If lifestyle changes don't bring blood pressure into the target range, a provider may adjust the testosterone dose, switch the delivery method, or add an antihypertensive medication. The choice of medication depends on each client's overall cardiovascular profile and is made by the prescribing provider.
When to Contact a Provider
Blood pressure emergencies are rare on TRT, but they require prompt attention. Contact the prescribing provider or seek medical care if any of the following occur:
-
Sustained blood pressure above 180/120 mm Hg
-
Severe headache with no clear cause
-
Chest pain or tightness
-
Shortness of breath at rest
-
Sudden vision changes
-
Confusion or difficulty speaking
Several updated 2025 testosterone labels state that the product is not recommended in men with uncontrolled hypertension (FDA, 2025). Men with controlled blood pressure on medication may still be considered for TRT, but this requires individualized assessment and closer monitoring by the prescribing provider.
Disclaimer: This blog post is intended for informational purposes only and should not be considered medical advice. Always consult a healthcare professional before making changes to your health routine.
FAQs
Does TRT raise blood pressure in every man who takes it?
Not every man on TRT experiences a blood pressure increase. The FDA's ambulatory monitoring data showed a class-wide average increase across all testosterone products, but the magnitude ranged from +1.7 to +4.9 mm Hg systolic depending on the formulation. Individual response depends on baseline health, hematocrit levels, body composition, and the specific product used.
How soon after starting TRT can blood pressure change?
Blood pressure shifts can appear within 4-16 weeks, based on the timeframes from the FDA's ambulatory monitoring studies. Men with preexisting elevated blood pressure or high hematocrit may notice changes sooner. Providers typically schedule follow-up blood work and blood pressure checks within the first 3 months of starting therapy.
When does hematocrit become a concern on TRT?
The Endocrine Society's 2018 guideline identifies elevated hematocrit as a threshold for clinical intervention, including dose adjustment or therapeutic phlebotomy. A 2025 retrospective study found that 23% of men on TRT developed elevated hematocrit, and 5% reached levels warranting intervention. The AUA recommends checking hematocrit before starting therapy and at each follow-up visit. A prescribing provider determines what level warrants action based on each client's overall clinical picture.
Can men with high blood pressure still take TRT?
Men with controlled hypertension may be candidates for TRT under close provider supervision. Several 2025 testosterone labels state that the product is not recommended for men with uncontrolled hypertension. Eligibility depends on an individualized assessment of cardiovascular risk, blood pressure control, and overall health. A prescribing provider monitors hematocrit, lipids, and cardiovascular status throughout treatment.
Is the TRAVERSE trial proof that TRT is safe for the heart?
The TRAVERSE trial's primary cardiac endpoint (major adverse cardiac events) was neutral, with no statistically significant difference between the testosterone and placebo groups. But the trial also found higher rates of atrial fibrillation (3.5% vs. 2.4%), pulmonary embolism (0.9% vs. 0.5%), and acute kidney injury (2.3% vs. 1.5%) in the testosterone group. The full picture includes both the neutral primary result and these secondary signals.
What type of blood pressure monitor is most accurate for home use?
Upper-arm cuff monitors are more accurate than wrist devices, according to the American Heart Association. For the most consistent readings, measure at the same time each day, sit upright with feet flat and the arm supported at heart level, wait 5 minutes before measuring, and take 2 readings 1 minute apart.
Share:
What To Expect At A TRT Consultation For First Timers