

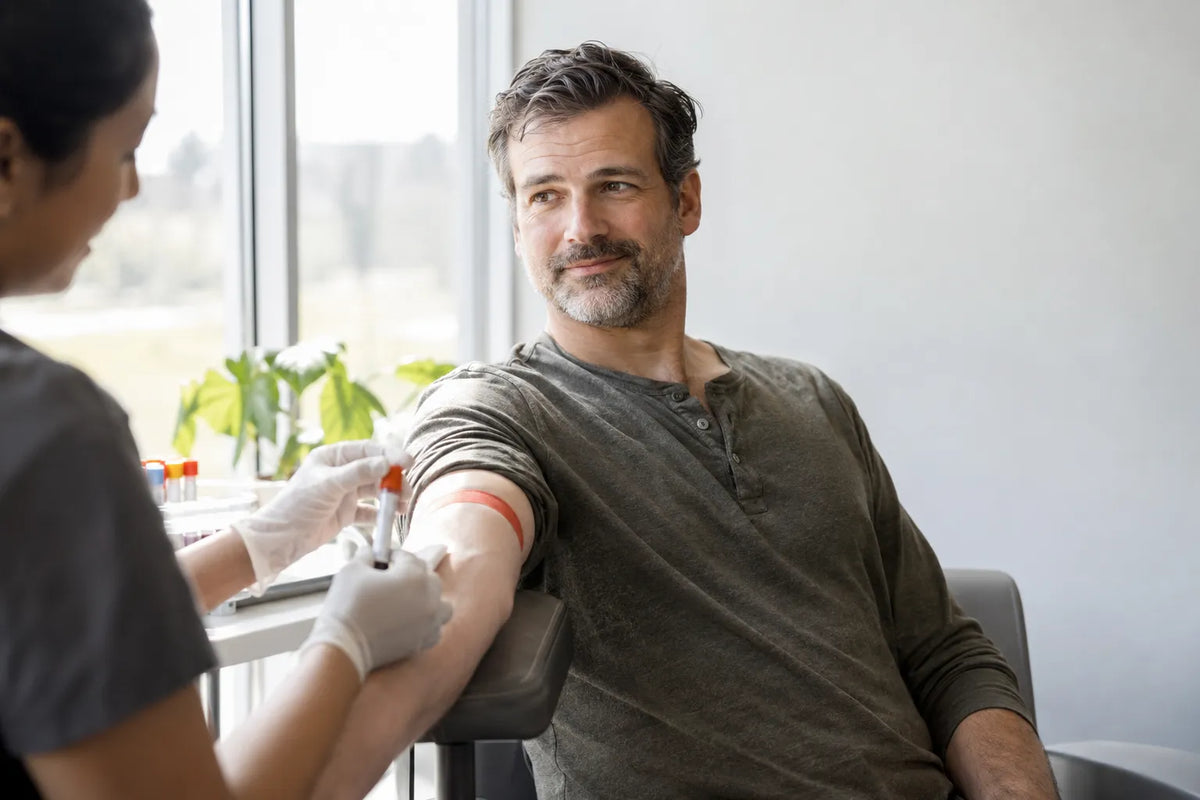
A standard full blood test usually doesn't check testosterone. The routine panels most people get, a complete blood count and a metabolic panel, measure blood cells, electrolytes, kidney and liver markers, and glucose. None of them report a testosterone level. Testosterone has to be ordered as its own test, and for a reading worth trusting it is generally best drawn in the morning. A full blood test only checks testosterone when a testosterone test is added to the order. Marek Diagnostics runs testosterone as dedicated hormone tests and as lab bundles that pair the hormone with the supporting markers a provider needs.

Does a full blood test check testosterone?
A routine blood panel, a complete blood count and metabolic panel, doesn't include a testosterone result. Testosterone is a separate, morning-drawn blood test. Confirming low testosterone takes two early-morning total testosterone measurements plus symptoms, per the American Urological Association (Mulhall et al., 2018).
A standard full blood test reports on blood cells and body chemistry, not sex hormones. A complete blood count measures red cells, white cells, hemoglobin, hematocrit, and platelets. A metabolic panel covers glucose, electrolytes, kidney markers like BUN and creatinine, liver enzymes such as ALT and AST, and total protein. That's useful information, but no testosterone value appears on either report.
One marker on the blood count, hematocrit, matters later for anyone on testosterone therapy. On its own, though, it says nothing about how much testosterone a person makes.
Which blood tests actually check testosterone?
Testosterone appears only when a testosterone-specific test is ordered. The anchor is a total testosterone test, the measure guidelines use to define the condition (Bhasin et al., 2018). Depending on the picture, a provider adds a few more markers:
-
LH and FSH. These two pituitary hormones can help point toward a testicular cause (high LH with low testosterone) versus a central, pituitary or hypothalamic cause (low or normal LH with low testosterone).
-
A prolactin test. High prolactin can lower testosterone and libido and may warrant a pituitary workup.
-
Thyroid and metabolic markers when symptoms are vague. If testosterone reads normal but the person still feels off, a provider looks past it, at thyroid function, blood sugar, and other drivers.
Total testosterone vs free testosterone
Total testosterone counts the hormone bound to proteins plus the small free fraction. Free testosterone is the fraction not bound to proteins, and with the loosely bound portion it makes up what may be available to tissues. The Endocrine Society recommends measuring free testosterone when total sits near the cutoff or when binding proteins are off (Bhasin et al., 2018). Binding shifts with age, thyroid disease, and body fat, which is where sex hormone-binding globulin comes in. When SHBG runs high or low, total testosterone can mislead, and free testosterone measured by a reliable method may give a more useful read.
Why testosterone is tested in the morning
Testosterone follows a daily rhythm, tending to be higher in the morning and drifting down as the day goes on, though this pattern can be less pronounced with age, so guidelines tie diagnosis to a morning draw. The AUA calls for two total testosterone measurements on separate days, both early in the morning, before any diagnosis is made (Mulhall et al., 2018). A single afternoon sample can read falsely low.
Assay quality isn't a footnote. Liquid chromatography-mass spectrometry (LC-MS/MS) is preferred for accuracy at the lower ranges, and repeating the test at the same lab with the same method keeps results comparable. For reference, the lower limit of normal in healthy young men, harmonized to the CDC standard, is 264 ng/dL (Bhasin et al., 2018).
What counts as low testosterone
Low testosterone means a low blood level together with symptoms, not a number read in isolation. The AUA uses a total testosterone below 300 ng/dL, confirmed on two early-morning draws, as a reasonable cutoff to support the diagnosis (Mulhall et al., 2018). Ranges differ by lab and assay, so the same value can land "low" at one lab and "normal" at another.
Levels also fall with age. Testosterone declines gradually in adult men, at a pace that varies from person to person. In the Baltimore Longitudinal Study of Aging, biochemically low testosterone became more common with age, seen in about 20% of men over 60 and roughly half of men over 80 (Harman et al., 2001). A low level on its own doesn't establish the clinical condition, which also requires symptoms. Age-related decline by itself isn't an approved reason for treatment. The FDA keeps a Limitation of Use stating testosterone products aren't approved for low testosterone due solely to aging (FDA, 2025).

Standard blood work vs a testosterone workup
The blood work most people already have and the tests that actually capture testosterone do different jobs.
|
What you order |
Main markers included |
Testosterone measured? |
|
Complete blood count (CBC) |
Red cells, white cells, hemoglobin, hematocrit, platelets |
No |
|
Metabolic panel (CMP) |
Glucose, electrolytes, kidney and liver markers, protein |
No |
|
Testosterone workup |
Total testosterone, free testosterone, SHBG, LH, FSH |
Yes |
The two are complementary. Routine panels track organ function and blood counts; a testosterone workup answers the hormone question. Ordering the first and assuming it covered the second is a common reason a low level can go unrecognized.
Testing before and during TRT
Testing doesn't stop at diagnosis. Before starting testosterone, a provider may set a baseline, which can include total and free testosterone, LH and FSH, hematocrit from a blood count, a PSA test where age-appropriate, and related labs, chosen for the individual. A pre-TRT panel groups common baseline markers into a single draw.
Once therapy is underway, monitoring watches for expected effects. Testosterone can raise hematocrit, and the Endocrine Society flags erythrocytosis, a hematocrit above 54%, as a point to lower the dose or pause treatment (Bhasin et al., 2018). Follow-up may include PSA and, when a provider judges it clinically relevant, sensitive estradiol, since testosterone converts to estradiol. A testosterone monitoring panel groups the markers a provider chooses to follow on a schedule they set.
Safety framing shifted recently. The TRAVERSE trial, in 5,246 middle-aged and older men with diagnosed deficiency and existing or high cardiac risk, found testosterone was noninferior to placebo for major adverse cardiac events, though the testosterone group had more atrial fibrillation (3.5% versus 2.4%) and more pulmonary embolism (0.9% versus 0.5%) (Lincoff et al., 2023).
Those signals mean cardiovascular risk is still weighed individually rather than assumed to be neutral. On that basis the FDA removed the older cardiovascular boxed warning in February 2025 and added a new warning that testosterone can raise blood pressure (FDA, 2025). Fertility is a separate matter. Testosterone therapy can suppress sperm production, the degree varies from man to man, and it isn't guaranteed to reverse, so anyone planning to conceive should raise it before starting.
How do you get your testosterone tested?
Getting an accurate answer comes down to ordering the right test and timing the draw. A morning total testosterone is the anchor, with free testosterone, SHBG, LH, FSH, and estradiol filling in the cause and context when the picture calls for it.
Testosterone testing options range from a single marker to grouped hormone panels, and results are meant to be read with a licensed provider, who can confirm an abnormal value on a second morning draw and advise on next steps. Where testosterone therapy is appropriate, it's prescribed only after evaluation by a licensed clinician and where state law permits, never automatically. The decision to start is made together with a provider, weighing individual risks, goals, and lab results.
A full blood test doesn't check testosterone by default. A routine panel skips the hormone, and even a testosterone result only means something when it's drawn in the morning, confirmed on a second sample, and read alongside symptoms by a provider. Ordering a dedicated testosterone test, or a hormone panel that bundles it with the right supporting markers, is how to get an answer worth acting on.
Disclaimer: This blog post is intended for informational purposes only and should not be considered medical advice. Always consult a healthcare professional before making changes to your health routine.
FAQs
Do I need a full blood test to check testosterone?
No. A routine full blood test, meaning a complete blood count and a metabolic panel, measures blood cells, electrolytes, kidney and liver function, and glucose, but not testosterone. Testosterone has to be ordered as a separate morning blood test.
Does a full blood test check testosterone during a routine physical? Not unless testosterone is specifically added to the order. A physical usually relies on a complete blood count and metabolic panel, which leave testosterone off, so the hormone is easy to miss without a targeted request.
What testosterone level is considered low?
The American Urological Association uses a total testosterone below 300 ng/dL, confirmed on two early-morning blood draws and paired with symptoms, as a reasonable cutoff. Reference ranges differ between labs, so results are read in context rather than against a single universal number.
Why does testosterone need to be tested in the morning?
Testosterone peaks in the morning and falls through the day, so an afternoon sample can read falsely low. The AUA and the Endocrine Society both call for a morning draw, repeated on a second morning to confirm before any diagnosis.
What is the difference between total and free testosterone?
Total testosterone measures the hormone bound to proteins plus the small free fraction, while free testosterone is the fraction not bound to proteins. The Endocrine Society recommends free testosterone when total is near the 264 ng/dL lower limit or when SHBG is abnormal.
Do I have to fast for a testosterone test?
Testosterone itself doesn't require fasting, though the Endocrine Society describes a fasting morning sample. Fasting matters if the same draw also includes glucose or a lipid panel.
Which blood tests monitor testosterone therapy?
Monitoring commonly includes repeat testosterone, hematocrit from a blood count, PSA where age-appropriate, and, when a provider judges it relevant, sensitive estradiol. The Endocrine Society flags a hematocrit above 54% as a reason to adjust or pause therapy.
Share:
Is A Hormone Test Painful? What Women Can Expect
Is TSH Higher On Your Period? What The Research Says